Corneal Ulcers: A Comprehensive Analysis of Causes, Clinical Implications, and Advanced Therapeutic Approaches

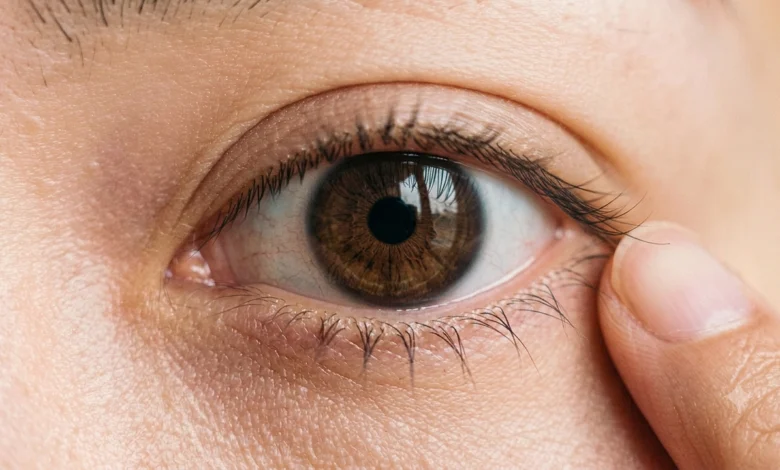
A corneal ulcer, medically classified as an ulcerative keratitis, represents a severe and potentially vision-threatening inflammatory condition characterized by an open sore on the cornea—the transparent, dome-shaped surface covering the front of the eye. This ocular pathology involves a defect in the corneal epithelium, often extending into the underlying stroma, and is typically precipitated by infectious agents, trauma, or chronic ocular surface diseases. While frequently categorized as a manageable condition when addressed promptly, the clinical reality is that corneal ulcers remain a leading cause of monocular blindness worldwide, necessitating a nuanced understanding of their pathophysiology and the imperative for rapid clinical intervention.
Understanding the Pathophysiology of Corneal Erosion
The cornea serves two critical functions: it acts as a physical barrier shielding the internal structures of the eye from external pathogens, and it serves as the primary refractive element, focusing light onto the retina. When the integrity of the corneal surface is compromised, the body’s natural protective mechanism—the tear film—is disrupted. A corneal ulcer occurs when an area of the corneal epithelium is breached, leading to an inflammatory response within the underlying stroma.
The progression of an ulcer is generally marked by localized cell death (necrosis) and the recruitment of inflammatory cells, such as neutrophils. This process creates a visible, often opaque, depression on the surface of the cornea. Left untreated, the infiltration of white blood cells and the enzymatic activity associated with the infection can lead to rapid thinning of the stroma, resulting in descemetoceles (protrusion of the Descemet’s membrane) or, in the most severe cases, frank corneal perforation, which constitutes a medical emergency.
Etiological Factors: From Infection to Traumatic Injury
The etiology of corneal ulcers is multifaceted, ranging from external environmental factors to systemic health complications. Clinical data suggests that the majority of cases are infectious in origin.
-
Infectious Keratitis: Bacteria, including Staphylococcus aureus, Pseudomonas aeruginosa, and Streptococcus pneumoniae, are the most common culprits. These pathogens often exploit minor abrasions to gain entry. Notably, the rise of improper contact lens hygiene has become a significant public health concern. Users who sleep in their lenses or fail to disinfect their cases are at a markedly higher risk of Acanthamoeba or Pseudomonas keratitis. Viral agents, particularly the herpes simplex virus (HSV) and varicella-zoster virus (VZV), are also major contributors, often leading to recurrent ulceration that can cause long-term stromal scarring.
-
Ocular Surface Trauma: Physical trauma caused by organic matter—such as tree branches or fingernails—or inorganic debris like metal shavings, can create deep lacerations. Furthermore, chemical burns, whether from acidic or alkaline substances, induce immediate necrotic damage to the corneal epithelium, stripping the eye of its primary defense mechanism.
-
Chronic Surface Instability: Conditions such as severe dry eye disease (keratoconjunctivitis sicca) deprive the cornea of the lubrication and antimicrobial properties provided by the tear film. Similarly, lagophthalmos—a condition where the eyelids cannot close completely—results in chronic exposure of the ocular surface, leading to desiccation and subsequent epithelial breakdown.
Clinical Presentation and Diagnostic Protocols
Patients presenting with corneal ulcers typically describe a sudden onset of symptoms, though the severity is often disproportionate to the size of the initial injury. Common clinical indicators include intense ocular pain, photophobia (extreme sensitivity to light), a persistent sensation of a foreign body, redness, and a notable decrease in visual acuity.
The diagnostic process, led by ophthalmologists, relies on specialized instrumentation. The slit-lamp biomicroscope is the gold standard for evaluation, allowing the physician to assess the depth, location, and nature of the infiltration. The application of fluorescein dye is a critical diagnostic step; the dye stains the denuded area of the cornea, highlighting the precise geometry of the ulcer when viewed under cobalt blue light. In cases where the ulcer appears resistant to standard treatments, corneal scrapings are performed for microbial culture and sensitivity testing. This allows clinicians to move beyond empirical treatment—prescribing broad-spectrum antibiotics—to targeted, pathogen-specific therapy.
The Timeline of Clinical Intervention
The prognosis for corneal ulcers is heavily dependent on the "time to treatment" window. The chronological progression of a typical case involves:
- Phase 1: The Initial Breach (Hours 0–24): The patient experiences mild irritation or foreign body sensation following trauma or contact lens wear.
- Phase 2: Acute Inflammation (Days 1–3): The epithelial defect expands. Pain becomes the predominant symptom, and the eye exhibits significant conjunctival injection (redness).
- Phase 3: Stromal Infiltration (Days 3–7): If untreated, the infection invades the deeper layers of the cornea. Visual acuity begins to decline rapidly due to stromal edema and the presence of pus in the anterior chamber (hypopyon).
- Phase 4: Resolution or Complication (Week 2 onwards): With aggressive treatment, the epithelium begins to regenerate. Without it, the structural integrity of the globe is at risk.
Global Impact and Public Health Data
Recent epidemiological surveys indicate that the incidence of microbial keratitis varies significantly by geographic region, often correlating with climate and socioeconomic status. In developed nations, contact lens wear is the primary driver, accounting for an estimated 60% of non-traumatic corneal ulcer cases. Conversely, in developing regions, agricultural trauma remains the dominant cause, often involving fungal infections which are notoriously difficult to treat and require prolonged therapeutic courses.
The economic burden of corneal ulcers is substantial, encompassing not only the direct costs of emergency ocular care and surgical intervention but also the indirect costs of productivity loss due to temporary or permanent visual impairment.
Advanced Therapeutic Strategies
Treatment is strictly individualized based on the causative agent. Bacterial ulcers are typically managed with intensive topical antibiotic regimens, often requiring round-the-clock administration in the first 48 hours. Fungal keratitis requires topical antifungal agents such as natamycin or voriconazole, while herpetic ulcers necessitate antiviral drops or oral medication.
A critical point of caution in clinical management is the use of corticosteroids. While they are powerful tools to suppress the inflammatory response and reduce scarring, their premature or improper use in the presence of an active infection can exacerbate the condition by suppressing the immune system’s ability to fight the pathogen. They are only introduced under strict specialist supervision once the infection is under control.
Long-term Implications: Beyond the Healing Phase
Even after the infection has been successfully eradicated, the ocular surface may face long-term consequences. Scarring, known as leucoma, can occur if the ulcer affected the central visual axis. This scarring scatters incoming light, leading to permanent visual degradation. In instances where the cornea has become significantly thinned or opacified, surgical intervention—most commonly a corneal transplant or keratoplasty—becomes the only viable option to restore functional vision.
The psychological impact of sudden vision loss, even if temporary, cannot be understated. Patients report significant anxiety and distress during the treatment period, highlighting the need for comprehensive patient counseling and support systems.
Conclusion: The Vitality of Prevention and Early Detection
The clinical community emphasizes that the prevention of corneal ulcers is largely a matter of ocular hygiene and safety. The use of protective eyewear in industrial or high-risk environments and the strict adherence to contact lens maintenance protocols are the most effective measures to reduce the incidence of this condition.
Ultimately, the message for patients remains clear: any persistent redness, pain, or visual disturbance following ocular irritation should not be ignored. The difference between a complete recovery and permanent visual impairment often rests on the speed with which a patient seeks professional medical evaluation. As diagnostic technologies continue to evolve, including the use of in-vivo confocal microscopy for real-time visualization of pathogens, the management of corneal ulcers is becoming increasingly precise, offering better outcomes for patients worldwide.
Related posts: